Start with the claim, not the category name
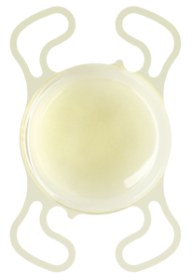
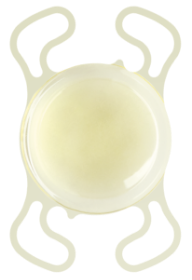
Bausch + Lomb describes LuxSmart as a premium lens for continuous distance and intermediate vision, with a potentially monofocal-like visual-symptom profile. Its Pure Refractive Optics design uses differently shaped central and peripheral regions to broaden focus without diffractive rings.
The central design combines spherical aberrations of opposite signs: different parts of the lens focus rays differently. This is an optical method, not a guarantee that contrast will be unchanged or every light source will look normal. A graph predicting acuity from laboratory measurements is not a randomized patient comparison with Vivity.
The manufacturer lists hydrophobic LuxSmart with UV/violet filtering and LuxSmart Crystal with UV filtering. This review does not pool every filter version, toric variant or the different LuxLife design as though they were one exact product.
What the main patient studies show
| Study | Useful finding and limitation |
|---|---|
| 2021: 12 LuxSmart patients versus 12 Akreos patients | The report describes random selection between lenses, but gives limited detail on allocation safeguards. At three months, intermediate chart vision was better with LuxSmart; half of its patients still depended on glasses for near tasks. Too small to establish equal halo risk. |
| 2023: 30 bilaterally implanted patients, six months | No concurrent control. Distance and intermediate vision were useful, but the discussion reports that 76% still needed glasses for reading. Symptom answers came from 28 people; two reported severe halos. Bausch + Lomb sponsored the study. |
| 2024: 20 patients, three months, mini-monovision | One eye was planned at distance and the other around −0.50 D. Seven people did not report complete glasses independence. Results concern a two-eye strategy—not LuxSmart alone. |
These are different groups with different targets, follow-up and questionnaires. Their percentages should not be averaged into one personal forecast. The 2021 and 2024 authors declared no conflicts; the 2023 report names an investigator relationship with Bausch + Lomb.
The 2024 paper has contradictions worth showing
Its abstract gives mean binocular uncorrected near acuity as 0.12 logMAR, while the results text and table give 0.32. Those are materially different reading results. We do not select the more favorable number and present it as settled.
The text says five of twenty people had frequent halos and glare. Its table lists two answering ‘often’ and one ‘always’ for each symptom—three of twenty. Without clarification, a single exact frequent-symptom percentage is unreliable. ‘Not incapacitating’ does not mean ‘not present’. There is also inconsistent reporting of the achieved near-eye refraction.
The text may be combining people affected by either symptom, whereas the table counts each symptom separately; it does not make that distinction clear. We therefore avoid a single precise frequent-symptom rate, rather than declaring the difference a proven arithmetic error.
These reporting issues do not prove that the lens is poor. They lower confidence in specific numerical claims from this paper and show why the full report matters more than a promotional summary.
A larger randomized trial is registered—not yet a result
NCT06105190 compares LuxSmart with LuxGood in a randomized, double-masked study. The public record checked on 11 October 2026 lists 251 actual participants, industry sponsor Cutting Edge SAS, and no posted results. Its last update is February 2025 and status remains active, not recruiting. An estimated completion date that has passed is not proof that findings are available.
That planned design could provide a more reliable comparison. Until its results are public and checked, it cannot be used to claim superiority or equal symptom risk. We did not verify a LuxSmart-specific FDA SSED; evidence from enVista or another Bausch + Lomb lens is not a substitute. Approvals and versions vary by country.
What we can—and cannot—conclude
Evidence supports a plausible intermediate-vision benefit in selected cataract patients. The strength is limited for precise glasses-independence forecasts, long-term safety and claims of monofocal-equivalent symptoms or contrast. Small studies reporting no statistically significant difference cannot rule out an important difference.
In the six-month study, contrast was compared with older normal-reference data, not a simultaneously implanted standard monofocal group; the reference range came from younger people. That is not a clean proof of equal contrast. The study also reported suspected vitreomacular traction in one patient, considered unlikely to be directly lens-caused: a favorable summary is not zero complications.
Important eye disease and previous surgery were excluded from the main early reports. A lens described as non-diffractive is not automatically suitable for an irregular cornea, glaucoma or retinal disease. Read how to read clinical data to separate a promising signal from a reliable promise.
The practical conclusion
LuxSmart can be discussed if you want more intermediate reach while accepting that near glasses may remain necessary. If mini-monovision is proposed, ask what it contributes and what it could cost in binocular comfort. Neither the design nor a surgeon testimonial establishes ‘no halos’. A balanced review is not a ranking of good and bad lenses.
Compare Eyhance, PureSee and ISOPURE through their own evidence, not cross-study satisfaction scores. Your screen distance and reading habits come first. Oleksii's discussion of enhanced monofocal options gives background, not a personal LuxSmart review.
- Which exact LuxSmart version and focusing targets are proposed?
- What should I expect for sustained reading at my preferred distance?
- What clinical findings or night-driving priorities might change the choice?
Sources and their limits
- Official LuxSmart site and product details: claims, optical explanation and filter versions; laboratory predictions and testimonials are not controlled clinical outcomes.
- Campos et al, 2021: full comparative report, 24 people total, three months; small sample and limited allocation reporting.
- Stodulka and Pracharova, 2023: full two-center observational report, 30 bilaterally implanted patients, six months; manufacturer-sponsored, no concurrent control.
- Campos et al, 2024 mini-monovision report: full report, 20 people, three months; internal near-acuity, symptom and refraction discrepancies noted.
- NCT06105190: current public randomized-study record checked; no posted results, not additional proof of effectiveness.
Educational information—not a diagnosis or medical prescription. An eye-care professional must assess your eyes and medical suitability before treatment or surgery.